

There Is a Difference – and It Matters
If you have been taking anti-inflammatories for your knee for six months, you have been managing your pain.
If you have had two cortisone injections in your hip and the third one is already wearing off faster than the second, you have been managing your pain.
If you stretch every morning for your heel and it helps for an hour and then comes back, you have been managing your pain.
Management is not nothing. In the early stages of joint pain – the first few weeks, when tissue is acutely inflamed and the body is in a normal post-injury state – management is the right approach. Rest. Anti-inflammatories. Cortisone when appropriate. Physical therapy to rebuild supporting structure.
But there is a clinical point at which the disease transitions. The acute inflammatory phase resolves. A different, slower process takes over – one driven not by inflammation but by a vascular mechanism that pain management does not reach. At that point, continuing to manage is not the same as treating. And the gap between the two is why so many patients with chronic joint pain spend years in partial relief, wondering why nothing holds.
What Happens When Pain Becomes Chronic
The transition from acute to chronic is not arbitrary. It happens at the tissue level.
In acute joint pain – the first six to twelve weeks – the tissue is inflamed. Cytokines are elevated. The synovial membrane is thickened and hyperemic. This is the phase where anti-inflammatory treatment has its highest value. Cortisone suppresses the acute response effectively. NSAIDs reduce the systemic inflammatory load. Physical therapy manages secondary deconditioning.
After roughly three months of persistent pain, the tissue picture changes. The acute inflammatory infiltrate resolves or diminishes significantly. What takes its place is a degenerative process characterized by synovial neovascularization – the growth of abnormal new blood vessels into the periarticular tissue, the synovial membrane, and the tendons around the joint. These vessels bring sensory nerve fibers with them. The nerve fibers are a direct structural pain source embedded in the tissue.
This neovascular network has no meaningful inflammatory component to suppress. It does not respond to cortisone. It does not regress with NSAIDs. It is not addressed by physical therapy, which works on muscle, load, and function – not on vessel biology.
Managing pain at this stage means applying the right tools to the wrong problem. The tools keep working – partially, temporarily – because they address secondary features of the disease. They do not address the primary driver.
External resource: Synovial neovascularization and chronic musculoskeletal pain – JVIR
Why This Matters More for Patients With Diabetes – National Diabetes Month
November is National Diabetes Month – and the connection between diabetes and chronic joint pain is one of the most clinically important and least discussed relationships in musculoskeletal medicine.
Diabetes accelerates joint degeneration through multiple, overlapping mechanisms:
Advanced Glycation End-Products (AGEs)
Elevated blood glucose over time produces AGEs – compounds that cross-link collagen in cartilage, making it brittle and less resilient under mechanical load. Cartilage in diabetic patients degrades faster, and the degradation is less reversible. The joint OA trajectory is accelerated.
Microvascular Disease
Diabetic microvascular disease impairs the small vessel supply to periarticular tissue. Cartilage, which already has no direct blood supply and depends on diffusion from the synovial fluid, is particularly vulnerable. Reduced microvascular health slows cartilage maintenance and repair.
Peripheral Neuropathy and Proprioceptive Loss
Diabetic peripheral neuropathy reduces the proprioceptive feedback that normally regulates joint loading mechanics. Without accurate feedback, patients load joints abnormally – accelerating mechanical wear and increasing the rate of degenerative change.
Pharmacological Conflicts
Diabetic patients face compounding pharmacological constraints. Long-term NSAID use carries renal risks in a population already prone to diabetic nephropathy. Repeated corticosteroid injections produce transient blood glucose elevation that can be clinically significant in patients with poorly controlled diabetes. The two most common pain management tools carry elevated risks in exactly the population that needs them most.
The result is a subset of diabetic patients with chronic joint pain – frequently in the knee, hip, or foot – who are in the management loop without a clear route to treatment, because the standard treatment tools carry risks that their metabolic profile does not accommodate.
External resource: National Diabetes Month – American Diabetes Association
What Treatment Actually Looks Like
Treatment – as distinct from management – addresses the primary driver of the pain. In chronic joint pain with confirmed neovascularization, the primary driver is vascular. The treatment is vascular.
Heart Vascular and Leg Center offers three minimally invasive procedures that treat the neovascular mechanism directly:
Genicular Artery Embolization (GAE) – Chronic Knee Pain
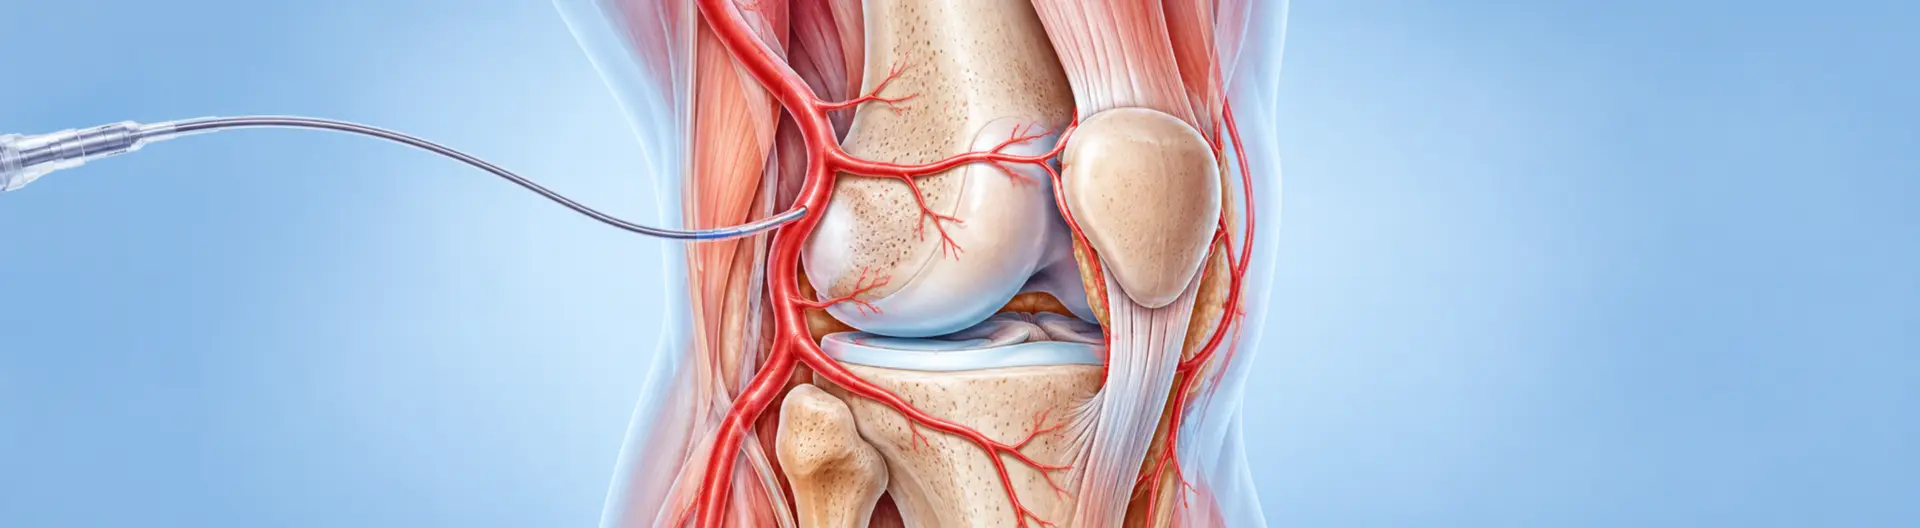
GAE uses a catheter to selectively reduce blood flow to the neovascular network in the knee’s synovial tissue. The abnormal vessels regress. The sensory nerve fibers lose their vascular support. Pain signals quiet. The procedure is outpatient, does not require general anesthesia, and does not alter joint anatomy.
GAE is particularly appropriate for diabetic patients who have contraindications to prolonged NSAID use or repeated cortisone, and who have mild to moderate knee OA with confirmed neovascular flow on imaging.
Read also: Genicular Artery Embolization – Knee Pain Treatment Detail
TAME – Chronic Shoulder and Hip Pain
Targeted Arterial Micro-Embolization applies the same catheter-based vascular approach to the shoulder and hip. Chronic shoulder tendinopathy with neovascularization that has failed conservative care, and chronic hip pain – trochanteric bursitis, hip OA in the mild to moderate range – are the clinical targets.
Like GAE, TAME does not require general anesthesia and does not alter joint anatomy. The treatment effect builds over six to twelve weeks as the neovascular network regresses.
Read also: Chronic Shoulder Pain and TAME
Plantar Fascia Embolization (PFE) – Chronic Heel Pain
PFE addresses the neovascular mechanism in chronic plantar fasciosis – the degenerative form of plantar fasciitis that persists beyond three months and stops responding to cortisone. Diabetic patients with chronic heel pain and peripheral neuropathy often have a neovascular component in the plantar fascia that drives the pain cycle independently of the neuropathic component. PFE addresses the vascular side of that dual mechanism.
Read also: Chronic Heel and Foot Pain – Plantar Fascia Embolization
The Right Time to Transition From Management to Treatment
The clinical signal that management has reached its ceiling is consistent. It looks like this:
- Cortisone injections that used to last three months now last three weeks
- NSAIDs provide partial relief but cannot be used long-term due to GI or renal concerns
- Physical therapy maintains function but does not reduce baseline pain
- The pain has been present for more than three months without a clear trajectory toward resolution
- Imaging shows no new structural change, but pain severity has increased
When that pattern is present, continuing to cycle through management tools is not a conservative strategy. It is a delay in appropriate treatment. The neovascular mechanism has been active long enough to be the dominant pain driver, and the tools being applied do not reach it.
A vascular evaluation – power Doppler ultrasound to confirm neovascular flow – answers the question directly. If neovascularization is present and active, treatment rather than continued management is the appropriate next step.
External resource: Chronic pain management versus interventional treatment – Society of Interventional Radiology
A Note on “Waiting Until It Gets Bad Enough”
One of the most common reasons patients delay vascular evaluation is the belief that they should “wait until it gets bad enough” for a more significant intervention. This is a reasonable instinct for a certain class of intervention – surgery, for example, carries real procedural risk that justifies a high threshold.
It is not the right framework for minimally invasive procedures like GAE, TAME, and PFE. These procedures are outpatient, done under local anesthesia, and carry low procedural risk. Their candidacy window is specifically the early-to-middle chronic phase – mild to moderate disease with confirmed neovascularization. Waiting for the disease to advance does not improve candidacy. In most cases, it narrows it: advanced structural loss shifts the disease into surgical territory, and the minimally invasive vascular option is no longer the right tool.
The question is not “is this bad enough.” It is “is this the right mechanism, and is this the right stage.”
Frequently Asked Questions
How do I know if I have neovascularization?
Power Doppler ultrasound is the primary imaging modality for identifying neovascular flow in periarticular tissue. It is a non-invasive, in-office study. If you have chronic joint pain lasting more than three months that has not responded adequately to conservative treatment, a vascular evaluation including Doppler imaging is the appropriate next step.
My doctor says I need to keep trying cortisone before anything else – is that right?
Cortisone is appropriate in the acute and early chronic phases of joint pain. If you have already had two or more cortisone injections with progressively shorter relief windows, the clinical pattern suggests the vascular mechanism is now dominant. Continuing injections at that point addresses a secondary feature rather than the primary driver. A vascular evaluation is a reasonable next step alongside, not instead of, your primary care.
Are GAE, TAME, and PFE appropriate for diabetic patients?
Yes – and they are often particularly well-suited for diabetic patients who have contraindications to prolonged NSAID use or repeated cortisone. The procedures do not carry the renal risks of NSAIDs or the glucose elevation associated with corticosteroid injections. Pre-procedure evaluation will assess your complete clinical and metabolic picture.
Does insurance cover these procedures?
Coverage varies by insurer, plan, and procedure. Our team verifies benefits prior to procedure and provides clear information on what to expect. Call 661-324-4100 for a benefits discussion.
What if I need surgery eventually – do these procedures affect that?
No. GAE, TAME, and PFE are vascular procedures that do not alter joint anatomy. They do not affect the technical feasibility of knee replacement, hip replacement, or other orthopedic surgeries if those become appropriate at a later stage.
Related Pages
- Genicular Artery Embolization – Knee Pain
- Chronic Shoulder Pain and TAME
- Chronic Heel and Foot Pain – PFE
- Contact and Appointments
Sources and External References
- American Diabetes Association – National Diabetes Month
- Journal of Vascular and Interventional Radiology (JVIR)
- Society of Interventional Radiology – Musculoskeletal Pain
- Arthritis Foundation – Osteoarthritis and Treatment Options
- American College of Rheumatology – Joint Pain Guidelines
Find Out Whether You Are Managing or Treating Your Joint Pain
If you have been managing chronic joint pain for more than three months without lasting relief, a vascular evaluation can determine whether a minimally invasive procedure is the next right step.
Heart Vascular and Leg Center – Bakersfield, CA
Call 661-324-4100 or visit heartandleg.com. Appointments available. Referrals welcome.





Follow us on: